
Gingival recession
Recession, cervical wear, sensitivity and tissue phenotype are assessed together when planning restorative or orthodontic treatment.
What I assess
These representative clinical images illustrate conditions that may influence diagnosis, treatment sequencing and long-term maintenance. They are educational examples rather than photographs of my own patients.
Recession, cervical wear, sensitivity and tissue phenotype are assessed together when planning restorative or orthodontic treatment.

Margin position, ferrule, bone level and soft-tissue architecture may determine whether a tooth can be restored predictably.

Bone loss between molar roots changes prognosis, cleansability and the long-term value of complex restorative treatment.

Implants also require periodontal surveillance, with attention to inflammation, recession, cleansability and supporting bone.
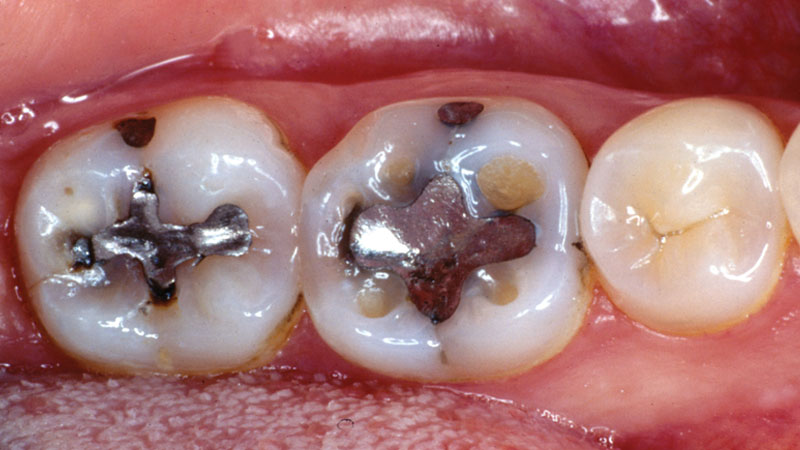
Open or deteriorating margins, recurrent caries and cracks in heavily restored teeth may alter the restorative prognosis.

A restoration may still look largely intact while recurrent disease develops locally at the tooth–restoration interface.
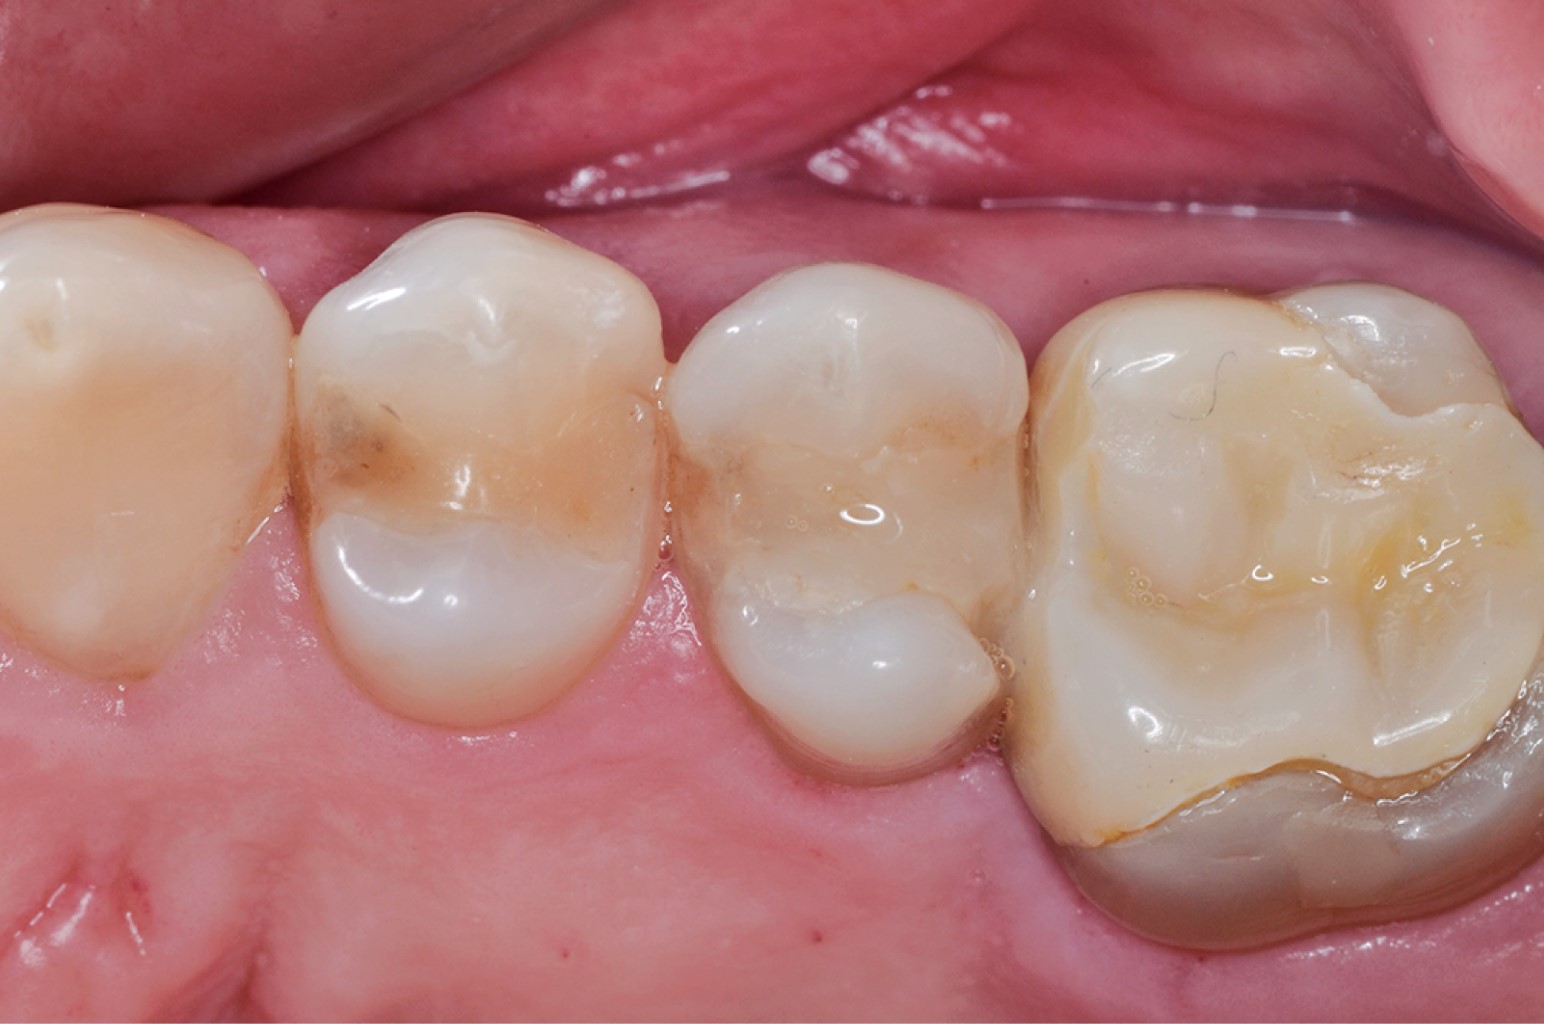
Marginal staining is interpreted alongside caries risk, marginal integrity, symptoms and radiographic findings rather than in isolation.

Visible coronal cracks require assessment of symptoms, remaining tooth structure, periodontal findings and the likely benefit of cuspal protection.

Clinical signs of tooth grinding may include worn incisal edges, flattening and functional wear that can influence occlusion, sensitivity, restorative planning and long-term monitoring.
Clinical philosophy
“The mouth is part of the body — not a structure to be treated in isolation.”
Oral health is influenced by far more than a single tooth. I consider periodontal inflammation and stability, supporting bone, tissue phenotype, medical history, medications, function, parafunctional habits, diet, restorative history, aesthetics and the patient’s ability to maintain treatment before deciding how — or whether — to intervene. For complex restorative care, the question is not simply whether a tooth can be restored, but whether the periodontal and restorative foundations make that treatment predictable and maintainable over time.
Modern digital tools support that thinking. Intraoral scanning and serial records can provide a repeatable way to compare change over time, including tooth wear patterns that may be associated with grinding or clenching, movement in tooth position and changes in gingival recession. Technology is used to support clinical judgement, not replace it.
My aim is conservative where possible: preserve healthy tooth structure, stabilise disease, correct contributing factors and choose restorative or orthodontic treatment only when it meaningfully improves prognosis, function or maintainability.